⚠️ Reward point withdrawals are temporarily unavailable. We're working on a fix.

BLOODWORK HELP

Back BLOODWORK HELP
Cycle planning, bloodwork, side effects, bulking and cutting, TRT and post-cycle therapy.

Joseph768

Newbie
Joined
Sep 27, 2026
Messages
1
Reaction score
0
Points
1.00
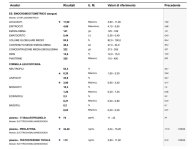
18yo male, 5 weeks into first Test E cycle, experiencing high E2 (72 pg/mL) and high Prolactin (34.40 ng/mL) with active early gyno symptoms (itching, tingling, and puffiness in both areolas for the last 6 days, no hard nodules felt yet). Strength and muscle fullness are increasing significantly. The issue could be due to the total dosage amount itself, or my initial protocol where for the first 4 weeks I ran an asymmetric rotation schedule (alternating 1mL and 0.5mL injections on Tuesdays and Fridays, total ~350-375mg/week of Testosterone Enanthate 250mg/mL). This highly asymmetric dosing likely caused severe hormonal spikes and up-regulated my aromatase activity. My week 5 bloodwork (drawn fasted, early morning, 84h post-injection) shows: Total Testosterone >15.00 ng/mL (Pre-cycle: 5.16), 17-Beta Estradiol at 72 pg/mL (Pre-cycle: 24, Range: 11-43), Prolactin at 34.40 ng/mL (Pre-cycle: 17.10, Range: 4.04-15.20), Hematocrit at 44% (Pre-cycle: 41%), and WBC at 11.60 Milam/cL (Pre-cycle: 7.60). I am trying to figure out the best corrective strategy. My current idea is to drop the dose to a stable 300mg/week split into perfectly symmetrical injections of 150mg (0.6mL) every Tuesday and Friday to flatten blood levels, and introduce Tamoxifen (Nolvadex) at 10mg ED to protect the breast tissue while preserving circulating E2. My plan would be to run this fixed protocol for 4 full weeks until October 23rd to let the Test E reach a clean steady-state, then draw blood at true trough (Friday morning, right before the injection) to see if E2/Prolactin drop naturally. I want to ask for your opinions: Is this a solid approach, or am I making a mistake? Should I use a low-dose AI (like Arimidex) instead of Nolvadex right away given the high numbers, or is dropping the test dose and switching to a symmetric schedule enough to fix the root cause? Any feedback on this strategy would be highly appreciated.
 

Attachments

  • IMG_20260927_000638_086.jpg
    IMG_20260927_000638_086.jpg
    83.3 KB · Views: 10
Hej, powiem ci z własnego doświadczenia. Kiedy biorę 250 mg testosteronu tygodniowo, jest dobrze, ale przy 500 mg poziom estrogenu gwałtownie rośnie i zaczynam odczuwać nieprzyjemne skutki uboczne – nadwrażliwość sutków, tworzenie się grudek i silne zatrzymanie wody. Eksemestan załatwia sprawę; inhibitory aromatazy są koniecznością, jeśli jesteś wrażliwy na wyższe dawki testosteronu. Pozdrawiam.
 
18yo male, 5 weeks into first Test E cycle, experiencing high E2 (72 pg/mL) and high Prolactin (34.40 ng/mL) with active early gyno symptoms (itching, tingling, and puffiness in both areolas for the last 6 days, no hard nodules felt yet). Strength and muscle fullness are increasing significantly. The issue could be due to the total dosage amount itself, or my initial protocol where for the first 4 weeks I ran an asymmetric rotation schedule (alternating 1mL and 0.5mL injections on Tuesdays and Fridays, total ~350-375mg/week of Testosterone Enanthate 250mg/mL). This highly asymmetric dosing likely caused severe hormonal spikes and up-regulated my aromatase activity. My week 5 bloodwork (drawn fasted, early morning, 84h post-injection) shows: Total Testosterone >15.00 ng/mL (Pre-cycle: 5.16), 17-Beta Estradiol at 72 pg/mL (Pre-cycle: 24, Range: 11-43), Prolactin at 34.40 ng/mL (Pre-cycle: 17.10, Range: 4.04-15.20), Hematocrit at 44% (Pre-cycle: 41%), and WBC at 11.60 Milam/cL (Pre-cycle: 7.60). I am trying to figure out the best corrective strategy. My current idea is to drop the dose to a stable 300mg/week split into perfectly symmetrical injections of 150mg (0.6mL) every Tuesday and Friday to flatten blood levels, and introduce Tamoxifen (Nolvadex) at 10mg ED to protect the breast tissue while preserving circulating E2. My plan would be to run this fixed protocol for 4 full weeks until October 23rd to let the Test E reach a clean steady-state, then draw blood at true trough (Friday morning, right before the injection) to see if E2/Prolactin drop naturally. I want to ask for your opinions: Is this a solid approach, or am I making a mistake? Should I use a low-dose AI (like Arimidex) instead of Nolvadex right away given the high numbers, or is dropping the test dose and switching to a symmetric schedule enough to fix the root cause? Any feedback on this strategy would be highly appreciated.
Hi,

Let’s start with the fact that if your estradiol is elevated, tamoxifen won’t help with that. It will only block estrogen receptors in the breast tissue so that the gyno doesn’t progress. But you need to address the main issue — reduce aromatization. For that, you need to use aromatase inhibitors such as anastrozole or exemestane.

Splitting the dose may potentially smooth out estradiol peaks somewhat, but if gyno has already started, it means you’re sensitive to estradiol. At the same time, if you block the receptors in the breast tissue with tamoxifen now, you won’t really be able to tell from how you feel whether anything has changed, apart from the estradiol level itself.

Most likely, you should take a minimal dose of an AI (for example, 12.5 mg of exemestane) twice a week and retest after a few weeks. I would keep estradiol around 30–40 pg/mL and then go by how you feel. If that level still causes problems, then bring it down to your previous 24 pg/mL.

As for prolactin, retest it together with estradiol after 24 hours of sexual abstinence.
 
18yo male, 5 weeks into first Test E cycle, experiencing high E2 (72 pg/mL) and high Prolactin (34.40 ng/mL) with active early gyno symptoms (itching, tingling, and puffiness in both areolas for the last 6 days, no hard nodules felt yet). Strength and muscle fullness are increasing significantly. The issue could be due to the total dosage amount itself, or my initial protocol where for the first 4 weeks I ran an asymmetric rotation schedule (alternating 1mL and 0.5mL injections on Tuesdays and Fridays, total ~350-375mg/week of Testosterone Enanthate 250mg/mL). This highly asymmetric dosing likely caused severe hormonal spikes and up-regulated my aromatase activity. My week 5 bloodwork (drawn fasted, early morning, 84h post-injection) shows: Total Testosterone >15.00 ng/mL (Pre-cycle: 5.16), 17-Beta Estradiol at 72 pg/mL (Pre-cycle: 24, Range: 11-43), Prolactin at 34.40 ng/mL (Pre-cycle: 17.10, Range: 4.04-15.20), Hematocrit at 44% (Pre-cycle: 41%), and WBC at 11.60 Milam/cL (Pre-cycle: 7.60). I am trying to figure out the best corrective strategy. My current idea is to drop the dose to a stable 300mg/week split into perfectly symmetrical injections of 150mg (0.6mL) every Tuesday and Friday to flatten blood levels, and introduce Tamoxifen (Nolvadex) at 10mg ED to protect the breast tissue while preserving circulating E2. My plan would be to run this fixed protocol for 4 full weeks until October 23rd to let the Test E reach a clean steady-state, then draw blood at true trough (Friday morning, right before the injection) to see if E2/Prolactin drop naturally. I want to ask for your opinions: Is this a solid approach, or am I making a mistake? Should I use a low-dose AI (like Arimidex) instead of Nolvadex right away given the high numbers, or is dropping the test dose and switching to a symmetric schedule enough to fix the root cause? Any feedback on this strategy would be highly appreciated.
The first thing that makes sense is to retest prolactin and macroprolactin, TSH + Free T4, under more standardized conditions: in the morning, preferably 2–3 hours after waking up, sit calmly for 20–30 minutes before the blood draw; the day before, avoid heavy training and significant breast/nipple stimulation, and as I wrote above — no orgasm for at least 24 hours.
 
Hej, powiem ci z własnego doświadczenia. Kiedy biorę 250 mg testosteronu tygodniowo, jest dobrze, ale przy 500 mg poziom estrogenu gwałtownie rośnie i zaczynam odczuwać nieprzyjemne skutki uboczne – nadwrażliwość sutków, tworzenie się grudek i silne zatrzymanie wody. Eksemestan załatwia sprawę; inhibitory aromatazy są koniecznością, jeśli jesteś wrażliwy na wyższe dawki testosteronu. Pozdrawiam.
That’s right — everyone’s sensitivity to estradiol is different. Some people get problems even on therapeutic doses of testosterone, while others have no issues with gynecomastia even when using 1000 mg per week. But that doesn’t mean estradiol isn’t causing other problems or that it doesn’t need to be monitored.
 
Back
Top