⚠️ Attention: the forum experienced a technical failure. We had to restore it from a September 29 backup, so some data added after that date may have been lost. We sincerely apologize for the inconvenience.

Expert Answered Cycle for combat sports

Back Cycle for combat sports
Planning your first cycle: what to run, how much, what to expect and what to avoid.

Deliicz

Newbie
Joined
Oct 12, 2026
Messages
6
Reaction score
1
Points
3.00
Hey guys,

I’m doing combat sports and interested about which peds are the best to use in that case.

I’m currently on 150mg Test E per week with 250IU HCG twice per week. Additionally taking 1.5mg Reta every five days to cut some weight. My BF is at the moment ~11-13%.

My goal ist to increase strength and endurance but without building a huge amount of muscle.
I thought to add low dose Drosta to my stack, and maybe later some small cycle (6 weeks) with var.
How do you think of that approach?

If my approach is fine how should I dose Drosta, and how long can I use it low dosed?
I’m a little bit concerned about the lipids(HDL, LDL). Will they hit hard, even in that small doses?

Thanks a lot in advance!
 
Hi mate,

I have a few follow-up questions:
  1. Your height, weight, and age.
  2. Do you compete or just train for yourself? Is it important for you to make a certain weight class? What kind of combat sport do you do?
  3. Do you want to use steroids purely for performance in combat sports, or are you also interested in aesthetics?
  4. Your lipid profile could potentially be affected by Drostanolone, but it will depend on the condition of your liver and your individual response in general. However, Oxandrolone will most likely inevitably lower your HDL and raise your LDL.
Hey Sam,

thanks for your response!
1. I’m 178cm, 78,5kg and 30y
2. I already have competed, but due to injury and lack of motivation I stopped for a while. Now I want to compete again. Reaching a specific weight class is not necessary. Could cut through a water cut, if necessary.
At the moment I’m doing just boxing, maybe switching back to MMA if my knee is getting better. But for now the focus is on Boxing.
3. I would say 65:35. Performance definitely, but would be great if aesthetics increases as well.
4. Can you recommend some supplements to support lipids while using that stack?

I attached some pics, so maybe you get a better overview of my physique.
Photos were taken in the morning, without pump, food etc.

PS: I don’t want to enhance my performance at any cost.
Some kind of Anabolics like Tren, NPP etc. I won’t take.
I want to do it as healthy as possible with minimal side effects.
 

Attachments

  • IMG_1307.jpeg
    IMG_1307.jpeg
    1.6 MB · Views: 23
  • IMG_1308.jpeg
    IMG_1308.jpeg
    1.3 MB · Views: 21
Last edited:
Okay mate, the picture is gradually becoming clearer. Thanks for the photos, they made things much easier to understand. But I might start untangling this from a different end than you expect...

First, your knee injury. How did you injure it, under what circumstances, what diagnosis were you given, and how long ago was it? The reason I’m asking is that cutting weight always increases the risk of injuries and recurring injuries.

As for your TRT, first it makes sense to assess whether you actually need it and what testosterone level this dosage gives you compared with your natural levels. Adding Drostanolone — yes, you can. Will you notice an improvement? Possibly, but you shouldn’t count on it as a guarantee. You could add around 150 mg and see whether there is any subjective effect after a few weeks.

Regarding your lipid profile, supplements can be used if the changes are minor. Send me your lipid panel results and I’ll advise you. If the changes are significant, it may be worth using ezetimibe or statins depending on the extent of those changes.

How long have you been using testosterone, and do you feel any improvement from it? That’s where we need to start. Then we should assess your bloodwork and from there put together a potential future protocol.
As for the knee, I may have phrased it more dramatically than I actually intended.
It wasn't injured by any specific action, more due to chronic overuse from wrestling, BJJ, long runs and not willing to stop training even if I’m in pain. It's likely genetic as well, since most people in my family have knee problems.
That was about a year ago; I had an MRI, but the doctor said it was just fluid buildup and inflammation.
It's already much better, though it still starts to ache now and then after long runs but for Boxing it’s sufficient.

I already did (small) bloodwork and after that I increased the dose from 125mg to 150mg.
If I add Drosta, I'll finish my cut and adjust my calories to maintenance or a slight surplus (about 200 calories).

I’ve been taking test for about seven weeks.
I wouldn't go so far as to say that I'm a completely different person, but I would say that it gives me a little more motivation and also helps me maintain muscle mass during the cut.

Thanks again for tailing your time!
 

Attachments

  • IMG_1296.jpeg
    IMG_1296.jpeg
    107.4 KB · Views: 24
Welcome bro!

If you had an MRI, could you send me the report? If your knee is still bothering you after a year, you need someone who can help you figure out the cause. There may be some compensations in your body that need to be corrected.

Okay, I understand you — testosterone improves your mental well-being and helps you maintain muscle. Are you planning to use it in cycles or stay on it permanently? The further strategy for adding anything else will depend on that.

And how is your blood pressure?
 
As far as I know, I didn’t receive a report for that at all. After the MRI, I got a CD, which I gave to the doctor. He looked at the MRI images and explained what was going on.
But I don’t have either the report or the CD at home. Either he kept the CD, or I threw it away because I didn’t think I’d need it again.🤦🏻‍♂️

Yes, you absolutely right with improving the mental/general well-being. That’s also one crucial aspect why I’m doing this.
I actually wanted to do it in longer cycles (maybe 6 months first) with lower doses (e.g., 150 Test/100–150 Drosta).
Just so I don’t suppress my natural production for too long and to avoid long-term side effects. For that, I’d also do a proper PCT with tamoxifen and clomiphene. That’s also one reason why I’m already using HCG.

My blood pressure is 115/73.
 
1. Injury.
It’s interesting that he didn’t provide any kind of report. The reason I focused on this is that if your knee has been bothering you for such a long time despite there being no acute injury, then this is chronic ongoing inflammation. Fluid around the joint or other tissues is simply a sign that inflammation is present, but there is no acute injury that can simply be treated conservatively or with medication. That’s why the doctor let you go. From a medical point of view, he was right. But for an athlete who trains, the story shouldn’t end there.

What was important for you to find out is that there is no serious mechanical injury. But the reason why the inflammation started is still unknown and hasn’t been addressed. If you don’t resolve this, there’s a high chance it will keep coming back, interfere with your training, and eventually the inflammation may start progressing. My advice is to find someone who understands what could have caused it. For that, you need to go through certain movement tests. Where exactly does it hurt? At the front below the knee, or for example on the outer side of the knee? In what position does it hurt, and what kind of pain is it?
2. Cycle.
Regarding 6-month cycles, there’s one nuance related to your goal that I want to warn you about so you keep it in mind. If your main goal is to maintain both muscle tone and your general energy and well-being, then no matter how low the doses are, recovery won’t be quick, and you’ll end up in a hormonal low for around 6 weeks anyway, at best. If your LH and FSH are at zero, it doesn’t really matter whether your total androgen load was 200 mg per week or 600 mg.

What I mean is that your idea is also not optimal from the perspective of avoiding long-term side effects. Six months is a long cycle. And afterward, for some time, based on clinical symptoms, you’ll essentially be hypogonadal and will also experience side effects from that. So you’ll basically get the “worst” from both sides.

In your place, I would consider TRT with HCG and monitor your semen analysis. If you’re planning to have children in the future, it’s better to think about this now and try to take the necessary preventive measures.
3. Heath.
Our conversation so far has been without the context of your current bloodwork, and that should also be taken into account. For now, I’m just giving you some thoughts to help determine the direction going forward, and I want you to look at the situation from different angles. Okay — your blood pressure is normal, which is great news.
 
Sorry for the late response, I was quite busy.
1. Injury
So, like I said, I’m not 100% sure anymore. It’s also quite possible that he gave me a report, but I threw it away because I thought I wouldn’t need it anymore. I checked my files again at home, but I don’t have the report or the CD with me.
In my opinion, the inflammation was caused by overuse and my own fault because I didn’t take any breaks from sports. Especially when it comes to BJJ and wrestling, which really take a toll on the knees.
When it hurts, it’s usually on the right side of the knee, next to the kneecap. It’s usually a sharp pain that occurs when I put weight on it.
2. Cycle
The 6-month mark was just a rough guideline on my part, because I thought that the longer I suppress my own testosterone, the harder it will be to get my natural production back to the level I had before I started TRT.
It’s clear that I’ll experience a hormonal dip after coming off the treatment, and that’s perfectly fine. The main thing is that my natural production fully recovers and, in the worst-case scenario, I don’t remain hypogonadal for the rest of my life.

Never say never, but I don't want kids. That's why I generally don't care much about my fertility.
So would you continue with the TRT as is? Should I add Drosta to the stack or not? And then take it long-term—meaning without PCT after, say, 6 months?
3. Health
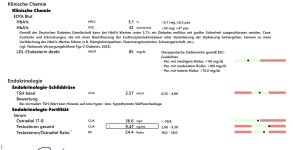
I had already included a few test results in a previous post. I know that’s not enough data for a meaningful analysis.
I plan to get a full checkup again in a few weeks—including a complete blood count, liver function tests, lipid profile, testosterone, free testosterone, E2, SHBG, and maybe LH and FSH.
 
  1. Regarding your knee — you said the pain is on the right side, but which leg is it, the left or the right? Quite often it could be a meniscus issue, which can cause sharp pain. Or it could be so-called “runner’s knee,” which I’ve also dealt with myself and am still trying to identify the exact cause of. My point is that if you ignore it, it may cause problems later and limit you. But that’s just advice.
  2. Usually, in terms of testosterone suppression, there may be no difference at all between 6 months and several years. And even if you want to do PCT after 6 months, first of all it will need to be fairly long, and secondly, after the PCT itself, if your goal is to restore your HPTA, you’ll still need to allow some additional time. During PCT, your LH and FSH levels may indeed return to normal, but once the stimulation is stopped, they can drop again. A common mistake is that people don’t wait for this and immediately start another cycle, suppressing the HPTA again. Overall, what you should do is a conceptual question — my task is to explain all the pros and cons of each approach so that you have a more complete understanding.

    PCT after 6 months will be fairly long, and after the PCT itself, if your goal is to restore HPTA function, you’ll still need to spend some time training naturally while doing bloodwork and checking what has happened after a few months. And if everything is okay, then you can start again. In the end, it may turn out that after a 6-month cycle you’ll have to spend another 4–5 months off. Then you have to ask whether using steroids makes sense at all.

    TRT allows you to avoid this problem and addresses the goals you’ve set. But you have to understand that in this case you should expect this protocol to dictate your lifestyle for many years, taking all the risks into account. If part of your goal is to improve your quality of life — motivation, drive, energy — and testosterone gives you that, then it doesn’t really make sense to stop it and then spend 4–5 months “in limbo” waiting for the next cycle.

    Adding Drosta makes sense as something to try. Evaluate the results after 4–6 weeks, monitor the necessary blood tests, and then see whether it suits you. You could also experiment with different things such as growth hormone or its secretagogues, MOTS-C, injectable L-carnitine, and evaluate each component individually to see whether you actually get any benefit from it. That’s what I would suggest.
  1. Yes, those tests don’t give the full picture. I can send you a list. But you absolutely don’t need to test total and free testosterone, SHBG, LH, and FSH — these tests aren’t very informative if you’re not on PCT. There are more important markers for assessing your health.
  2. Regarding fertility and having children — since I have some experience with this, I would approach it differently. This is what I suggest to everyone who thinks they won’t want children. I would get a semen analysis, and if everything looks good, simply freeze some sperm just in case. Right now you don’t want children, but later you may get married, and your wife could end up suffering because your selfishness leaves her without the chance to fulfill what may be her main purpose and the most important project of her life — having a child.

    I would look at things from the perspective that your opinion may change, and your life today isn’t the same as your life tomorrow, when there will be other variables that may matter much more than they do now. It’s just something to think about — everything changes, and it’s wise to consider this in advance.
 
Back
Top